Some medical ideas arrive wearing a white coat. Others kick down the laboratory door carrying a science-fiction megaphone. The human head transplant belongs firmly in the second category. For more than a decade, headlines have promised that the world’s first human head transplant is “almost here,” “about to happen,” or “just waiting for the right patient.” And yet, here we are, still attached to the original equipment.
So, could the world’s first human head transplant happen in the next two years? The honest answer is: almost certainly not in any medically accepted, ethically approved, survivable way. The idea remains one of the most controversial proposals in modern surgery, sitting at the crossroads of neurosurgery, organ transplantation, spinal cord repair, robotics, bioethics, and the human tendency to say, “What if?” before asking, “Should we?”
That does not mean the topic is pure fantasy. Surgeons have performed astonishing reconstructive procedures, including face transplants, hand transplants, and even a combined whole-eye and partial-face transplant. Researchers are also making progress in spinal cord injury treatment, nerve repair, regenerative medicine, and robotic surgery. But a human head transplant is not simply “a bigger transplant.” It is a biological mountain range with cliffs on every side.
What Does “Human Head Transplant” Actually Mean?
The phrase “human head transplant” is catchy, but medically awkward. Many experts prefer the term “body-to-head transplant” or “whole-body transplant,” because the patient’s brain and head would theoretically remain the seat of identity, memory, and consciousness, while the body would come from a donor.
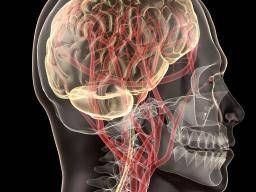
In simple terms, the proposed procedure would involve connecting a living person’s head to a donor body. That sounds like a movie pitch written during a thunderstorm, but the technical idea has been discussed in scientific papers, interviews, and speculative surgical proposals. The biggest goal would be to preserve blood flow to the brain, connect major tissues, manage immune rejection, and somehow restore communication between the brain and the new body through the spinal cord.
That last part is the brick wall. Modern medicine can connect blood vessels. It can transplant organs. It can reconstruct faces. It can stabilize the spine. But reliably reconnecting a severed human spinal cord so that movement, sensation, breathing control, bladder function, temperature regulation, and countless other signals work again? That is not currently available medicine. That is the dragon at the gate.
Why People Keep Talking About the First Human Head Transplant
The modern head transplant conversation became famous largely because of Italian neurosurgeon Sergio Canavero, who publicly claimed in the 2010s that the first human procedure could happen within a few years. His proposed project drew global attention, criticism, fascination, and enough dramatic headlines to power a small media factory.
One of the best-known potential volunteers was Valery Spiridonov, a Russian man with a severe muscle-wasting condition. The proposed operation did not take place. Canavero later claimed that rehearsals and experiments had demonstrated feasibility, including work involving cadavers, but those claims did not produce the kind of widely accepted clinical evidence that would move the procedure into mainstream medicine.
More recently, BrainBridge, a concept promoted by molecular biologist and science communicator Hashem Al-Ghaili, introduced a futuristic vision of AI-assisted robotic head transplantation. The concept video spread widely online, showing robotic systems performing an extremely complex transplant scenario. BrainBridge has suggested a longer timeline than two years, with public claims pointing closer to the next decade rather than immediate clinical use.
That difference matters. A concept video is not a clinical trial. A prototype is not a hospital-approved procedure. A viral animation is not evidence that a patient can survive, recover, and live well afterward. In medicine, the gap between “impressive demonstration” and “safe treatment” is wide enough to park several ambulances.
The Main Scientific Barriers
1. Reconnecting the Spinal Cord
The spinal cord is not an electrical cable that can be unplugged, taped together, and rebooted. It is a dense, living communication highway made of nerve fibers, supporting cells, chemical signals, blood supply, and delicate pathways. When spinal cord tissue is severely damaged, the body responds with inflammation, scarring, and molecular barriers that make nerve regrowth difficult.
Researchers are studying stem cells, biomaterials, nerve grafts, electrical stimulation, gene therapy, and rehabilitation methods to improve recovery after spinal cord injury. Some results are promising, especially in limited injuries and experimental settings. But reconnecting an entirely separated spinal cord at the neck and restoring full-body function remains far beyond current clinical capability.
2. Preventing Brain Injury
The brain is demanding. It wants oxygen and blood flow continuously, and it is not known for being patient. Any procedure that risks interrupting circulation to the brain must solve timing, temperature, perfusion, and protection problems with extreme precision. Even ordinary surgeries can become dangerous when the brain is involved. A head transplant would be brain-protection difficulty set to “boss level.”
3. Immune Rejection
Transplantation already requires careful immune management. Kidney, liver, heart, lung, hand, and face transplant recipients usually need immunosuppressive medications to reduce the risk of rejection. These medicines can be lifesaving, but they also increase vulnerability to infections and other complications.
A whole donor body would contain many tissues: skin, muscles, blood vessels, bones, nerves, organs, and immune cells. The immune challenge would be enormous. The question would not be simply, “Can the body accept the head?” It would also be, “Can the patient survive the immune consequences of receiving almost everything below the neck?” That is not a small paperwork problem. That is an entire medical weather system.
4. Breathing, Autonomic Function, and Basic Survival
The spinal cord helps manage far more than walking. It is involved in breathing control, blood pressure, digestion, temperature regulation, sexual function, bladder and bowel control, and pain signals. A patient could theoretically be kept alive with intensive support, but long-term quality of life would depend on restoring or replacing many automatic body functions.
Medicine can support patients through remarkable crises, but survival alone is not the same as success. A responsible clinical goal would require meaningful function, communication, comfort, and long-term stabilitynot merely a dramatic headline.
Ethical Barriers: The “Should We?” Question
Even if the technical problems improved, ethics would remain a massive hurdle. Human research requires informed consent, a reasonable risk-benefit balance, independent review, patient protection, and a credible scientific foundation. A first-in-human head transplant would challenge every part of that framework.
Who would qualify as a candidate? Someone with a terminal illness? Someone with paralysis? Someone whose brain is healthy but body is failing? What would count as a successful outcome? Survival for one day? One year? The ability to breathe independently? The ability to move? The ability to feel at home in a new body?
Then there is the donor side. A donor body would likely come from a person declared brain-dead, raising questions about organ allocation. In the current transplant system, donor organs are matched to patients based on medical urgency, compatibility, waiting time, and policy. Using an entire donor body for one experimental procedure could mean not using individual organs to save several other people. That ethical math is heavy, and nobody should pretend it fits neatly on a sticky note.
Legal and Regulatory Reality
In the United States, a procedure this experimental would face intense scrutiny from hospitals, institutional review boards, transplant authorities, regulators, malpractice insurers, and ethics committees. Surgeons cannot simply announce a history-making operation and reserve Operating Room 7.
Clinical research must be supported by preclinical data, safety planning, patient monitoring, and a clear scientific rationale. For something as radical as a human head transplant, regulators would likely demand extraordinary evidence before allowing a live patient attempt. At the moment, that evidence does not exist at the level needed for mainstream approval.
Could Robotics and AI Change the Timeline?
Robotics and artificial intelligence are already changing surgery. Robots can help surgeons make precise movements. AI can assist with imaging, planning, monitoring, and pattern recognition. These tools may improve transplant surgery and neurosurgery over time.
However, better tools do not automatically solve unsolved biology. A robot may cut or connect tissue with impressive precision, but it cannot magically make adult human spinal cord pathways regenerate in the correct order. AI may help plan a procedure, but it cannot waive the immune system’s objections. Technology can sharpen the knife, so to speak, but the body still has to heal.
That is why claims about AI-powered head transplantation should be viewed with curiosity and caution. The future may bring major breakthroughs in nerve repair and brain-body interfaces. But the next two years are a very short runway for a procedure that has not yet cleared the basic safety, function, ethics, and evidence hurdles.
What Recent Medical Breakthroughs Actually Tell Us
There are real reasons for optimism in reconstructive surgery. Face transplantation has helped some people regain appearance, function, and social confidence after devastating injuries. Hand transplants have shown that complex tissue can be transferred and rehabilitated. The combined whole-eye and partial-face transplant performed at NYU Langone demonstrated that surgeons can preserve and monitor incredibly delicate transplanted tissues in ways that once seemed impossible.
But these breakthroughs also teach humility. Face transplant patients require long-term care, immune suppression, rehabilitation, psychological support, and careful monitoring. Success is not instant. It is not a dramatic reveal with background music. It is years of appointments, setbacks, therapy, adaptation, and courage.
A head transplant would multiply those challenges. It would not be a single miracle moment. It would be a lifelong medical state, assuming the patient survived at all.
Could It Happen in the Next 2 Years?
Technically, someone somewhere could claim to attempt almost anything. But could the world’s first human head transplant happen in the next two years as a credible, ethically approved, medically successful procedure? The answer is no, based on today’s evidence.
The reasons are clear. Spinal cord reconnection is not solved. Immune rejection would be extreme. Donor allocation would be ethically explosive. Long-term survival and quality of life are unknown. Regulatory approval would be difficult. And the scientific community has not seen convincing evidence that the procedure is ready for a living human patient.
A more realistic timeline, if the field progresses at all, would involve smaller steps: better spinal cord repair, improved nerve regeneration, safer immunosuppression, more advanced brain-computer interfaces, better robotic microsurgery, and deeper experience with complex composite tissue transplants. The first true “head transplant” is not likely to appear suddenly. It would require decades of incremental breakthroughs stacking up like medical Lego bricks.
What Might Happen Instead?
The more realistic future may not be a human head transplant at all. It may be technologies that make the idea unnecessary.
For people with paralysis, spinal cord stimulation, regenerative therapies, advanced rehabilitation, neural implants, and brain-computer interfaces may restore more independence. For people with organ failure, better organ preservation, lab-grown tissues, xenotransplantation research, and improved donor systems may expand treatment options. For people with severe injuries, reconstructive transplantation may continue improving without requiring anything as extreme as whole-body replacement.
In other words, the future may not be “move the head to a new body.” It may be “repair the body, support the nervous system, replace damaged parts, and help people live better lives.” That path sounds less like a sci-fi trailer, but it is far more likely to help real patients.
Experience Notes: What This Topic Teaches Patients, Families, and Curious Readers
Following the story of the world’s first human head transplant can feel like standing between two doors. Behind one door is astonishing medical progress: surgeons restoring faces, scientists coaxing nerves to repair, engineers building robotic tools that make yesterday’s impossible look slightly less smug. Behind the other door is hype, where every concept video is treated like a hospital announcement and every bold prediction gets dressed up as destiny.
The first experience many readers have with this topic is surprise. The headline sounds so outrageous that people click just to confirm they read it correctly. Then comes the second reaction: “Wait, is this real?” That question is healthy. In medical science, skepticism is not cynicism; it is a seatbelt. It keeps excitement from flying through the windshield.
Patients and families dealing with paralysis, degenerative disease, or severe injury may experience the topic differently. For them, futuristic surgery is not just entertainment. It can touch real hope. That hope deserves respect. Nobody should mock people for wanting more time, more movement, less pain, or another chance at ordinary life. At the same time, hope must be protected from exaggeration. A headline promising a human head transplant in two years can create emotional whiplash if the science is nowhere near ready.
There is also the experience of watching medicine move slowly. To the public, slow progress can look frustrating. To researchers, slow progress often means safety. Before a therapy reaches patients, it must survive experiments, peer review, ethical review, funding problems, failed assumptions, revised methods, and clinical trials. That process is not glamorous, but it is the reason modern medicine is more than a collection of brave guesses.
Another important experience is learning how connected the body really is. A head transplant sounds like one dramatic connection point, but the human body is an orchestra. Blood vessels, nerves, hormones, immune cells, organs, muscles, skin, and the brain all play together. Change one section and the entire performance can wobble. The spinal cord is not just a wire. The immune system is not just a security guard. The brain is not just a passenger. Everything talks to everything else, usually in biochemical group chats we are still trying to read.
For writers, educators, and science communicators, this topic is a reminder to use careful language. “Could happen” is not the same as “will happen.” “Concept” is not the same as “clinical evidence.” “Successful experiment” needs context: successful in what model, for how long, and with what function? The more sensational the subject, the more boringly accurate the wording should be. Science loves wonder, but it gets grumpy when wonder borrows its lab coat without permission.
For readers, the best approach is balanced curiosity. Enjoy the big questions. Follow the breakthroughs. Ask what evidence exists. Look for expert consensus. Be cautious with viral claims. And remember that the most meaningful medical advances are not always the loudest ones. Sometimes the future arrives not as a head transplant, but as a better rehabilitation device, a safer anti-rejection drug, a smarter nerve graft, or a therapy that helps someone button a shirt again. That may not sound like science fiction. It sounds better: real life improving one hard-won step at a time.
Conclusion: A Future Worth Watching, But Not Betting the Neck On
The world’s first human head transplant remains one of medicine’s most provocative ideas. It challenges our understanding of identity, disability, death, transplantation, and the limits of surgical ambition. But the next two years are unlikely to deliver a legitimate, successful human head transplant. The barriers are not merely technical; they are biological, ethical, legal, psychological, and social.
Still, the conversation is useful when handled responsibly. It pushes people to learn about spinal cord injury, transplant medicine, robotics, immune rejection, and patient ethics. It reminds us that medicine advances through disciplined evidence, not dramatic countdowns. The real miracle may not be a head placed on a new body. It may be the quieter breakthroughs that help people keep, repair, or regain function in the bodies they already have.