Depression can feel like someone quietly unplugged the color from life. The coffee tastes flat, emails look like mountain ranges, and even choosing socks may require the emotional strength of a medieval knight. The good news is that depression is treatable, and for many people, antidepressant medications are an important part of getting back to steadier ground.
Antidepressants are prescription medications used to treat major depressive disorder and several related conditions, including anxiety disorders, panic disorder, obsessive-compulsive disorder, post-traumatic stress disorder, seasonal affective disorder, and some types of chronic pain. They are not “happy pills,” personality changers, or magic buttons. Instead, they help adjust brain chemical signaling over time so mood, sleep, appetite, energy, and concentration can improve.
This guide explains the major types of depression medications, how antidepressant drugs work, what side effects to expect, how doctors choose a medication, and what real-world treatment often feels like. It is educational, not personal medical advice. Depression care should always be guided by a licensed clinician, especially if symptoms are severe, suicidal thoughts appear, or medications are being started, stopped, or changed.
What Are Antidepressants?
Antidepressants are medications that influence neurotransmitters, the chemical messengers nerve cells use to communicate. The three neurotransmitters most often discussed in depression treatment are serotonin, norepinephrine, and dopamine. These chemicals affect mood, motivation, alertness, sleep, appetite, pain perception, and emotional regulation.
Depression is not simply “low serotonin,” despite what old commercials made many people believe. It is a complex condition involving genetics, stress biology, inflammation, hormones, sleep, thinking patterns, life events, and brain circuits. Antidepressant drugs do not fix one tiny broken switch. They help create conditions in the brain and body that make recovery more possible.
Many people use antidepressants together with psychotherapy, lifestyle changes, social support, and treatment for other health issues. That combination often works better than relying on medication alone, especially when depression is linked with grief, trauma, relationship stress, chronic illness, substance use, or burnout.
How Do Antidepressant Drugs Work?
Most antidepressants change how long neurotransmitters remain available between nerve cells. For example, selective serotonin reuptake inhibitors, or SSRIs, slow the reabsorption of serotonin. Serotonin-norepinephrine reuptake inhibitors, or SNRIs, affect both serotonin and norepinephrine. Other antidepressants work through dopamine, glutamate, melatonin-related pathways, or several receptors at once.
Here is the part that surprises many people: antidepressants usually do not work overnight. Some side effects can appear within days, which feels wildly unfair, while mood benefits may take two to six weeks or longer. Early improvements may show up as slightly better sleep, fewer crying spells, a little more patience, or the ability to complete small tasks. The dramatic movie-scene turnaround is rare. Real recovery is usually more like a dimmer switch than a light switch.
Main Types of Depression Medications
1. SSRIs: The Common First Choice
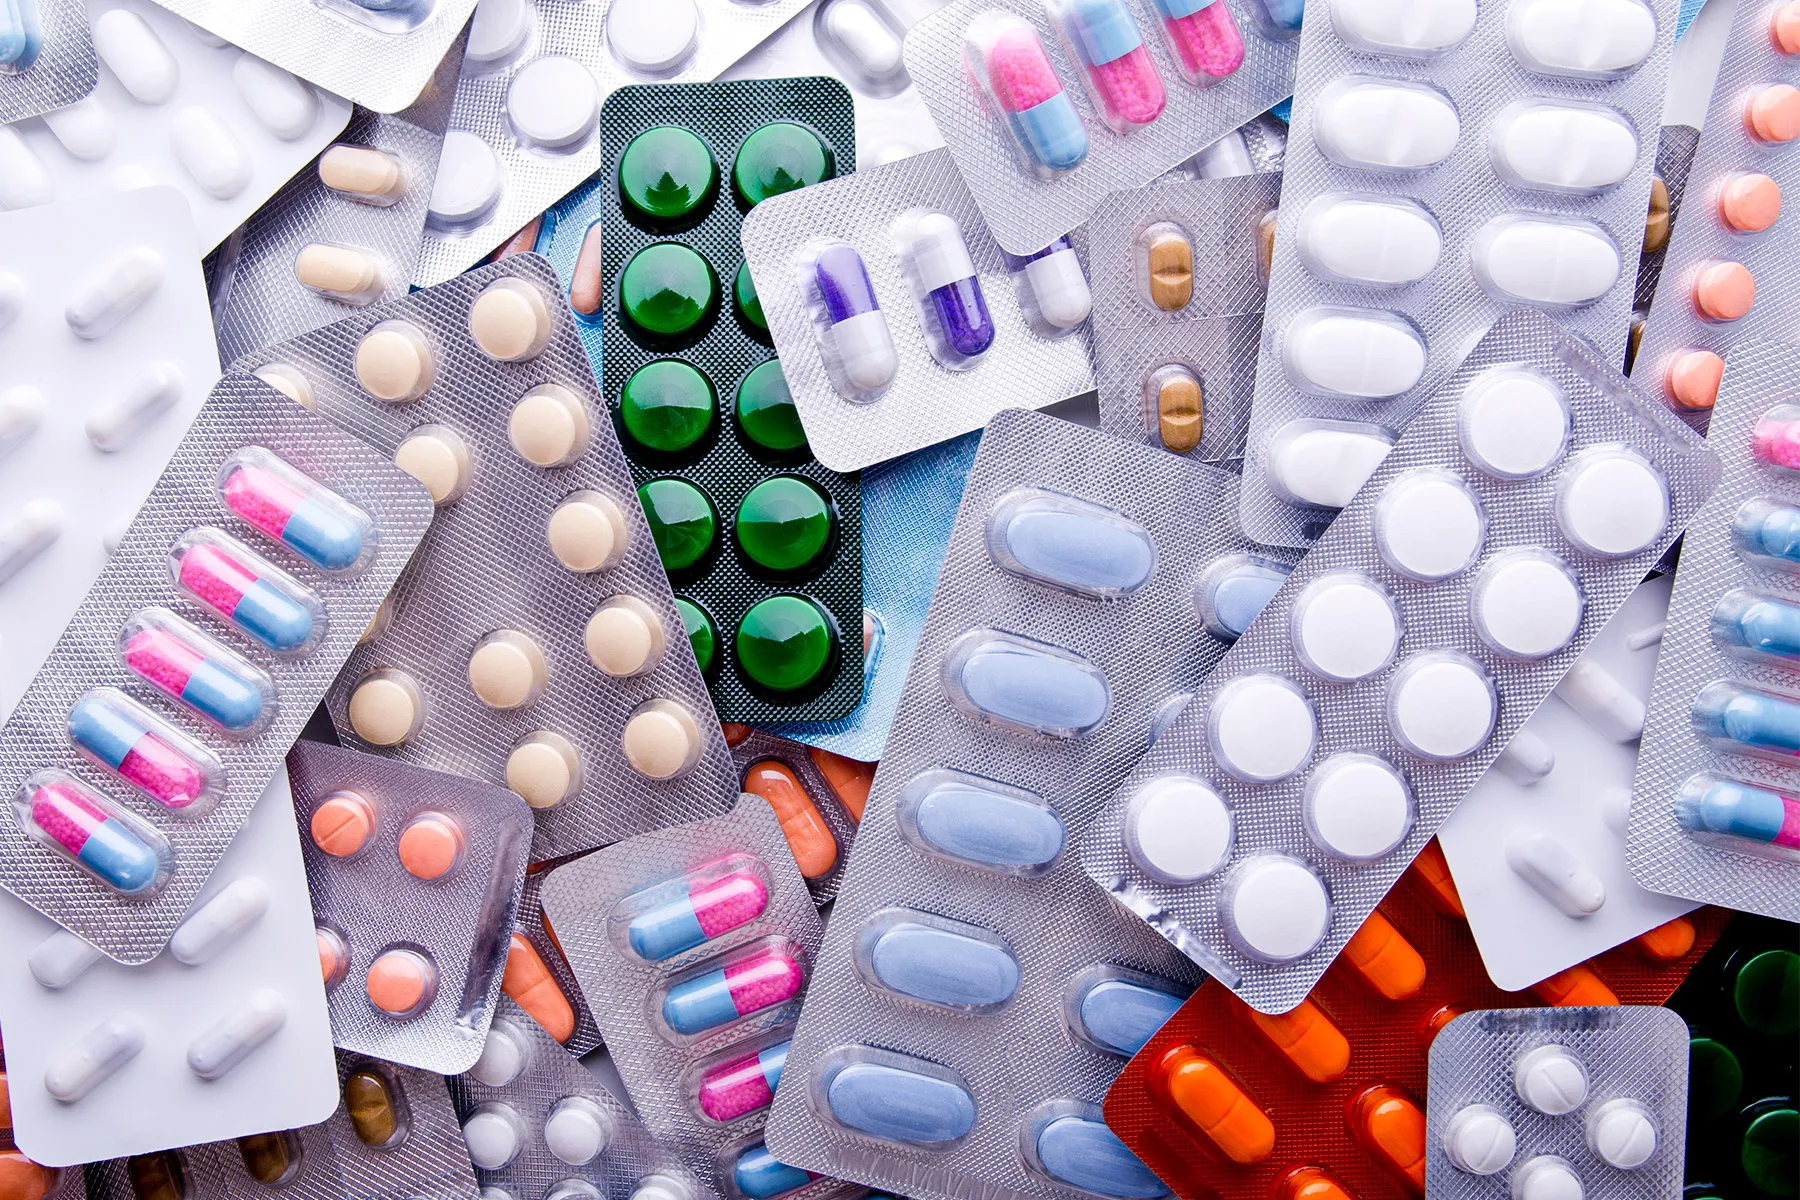
SSRIs are among the most commonly prescribed antidepressants because they are effective for many people and generally have a more tolerable side effect profile than older antidepressants. Common examples include sertraline, fluoxetine, escitalopram, citalopram, paroxetine, and fluvoxamine.
Doctors often consider SSRIs for depression with anxiety, panic attacks, obsessive thoughts, or emotional rumination. Possible side effects include nausea, headache, sleep changes, sweating, dry mouth, sexual side effects, and temporary stomach upset. Some people feel energized; others feel sleepy. The body, apparently, enjoys keeping clinicians humble.
2. SNRIs: Helpful for Mood, Energy, and Pain
SNRIs affect serotonin and norepinephrine. Common examples include venlafaxine, desvenlafaxine, and duloxetine. These medications may be useful when depression comes with fatigue, poor concentration, anxiety, or certain pain conditions such as nerve pain or fibromyalgia.
Potential side effects include nausea, dizziness, dry mouth, sweating, insomnia, sexual side effects, and increased blood pressure in some people. Because norepinephrine is involved, doctors may monitor blood pressure more closely, especially at higher doses.
3. NDRIs: Dopamine and Norepinephrine Support
Bupropion is the best-known norepinephrine-dopamine reuptake inhibitor. It is often considered when depression involves low motivation, low energy, difficulty concentrating, or concerns about sexual side effects from SSRIs or SNRIs. Bupropion is also used for seasonal affective disorder and smoking cessation.
It may cause insomnia, dry mouth, anxiety, tremor, or appetite changes. It is not usually recommended for people with seizure disorders or certain eating disorders because it can increase seizure risk. For the right patient, however, it can feel less emotionally “flattening” than some serotonin-focused medications.
4. Atypical Antidepressants
Atypical antidepressants do not fit neatly into the SSRI or SNRI categories. Mirtazapine, trazodone, vortioxetine, vilazodone, and dextromethorphan-bupropion are examples. Each has a distinct profile.
Mirtazapine may be helpful when depression comes with insomnia, weight loss, or poor appetite, though it can cause sleepiness and weight gain. Trazodone is often used at lower doses for sleep. Vortioxetine may be considered when cognitive symptoms, such as brain fog, are prominent. Dextromethorphan-bupropion is a newer oral option for major depressive disorder in adults and works partly through glutamate-related pathways.
5. TCAs: Older but Still Useful
Tricyclic antidepressants, or TCAs, include amitriptyline, nortriptyline, imipramine, and clomipramine. These older medications can be effective, but they tend to cause more side effects than newer drugs. They may be used when other medications have not worked or when depression overlaps with chronic pain, migraine prevention, or sleep problems.
Possible side effects include dry mouth, constipation, blurred vision, drowsiness, weight gain, dizziness, and heart rhythm concerns. Because overdose can be dangerous, clinicians prescribe TCAs carefully and may order heart monitoring for certain patients.
6. MAOIs: Powerful but High-Maintenance
Monoamine oxidase inhibitors, or MAOIs, include phenelzine, tranylcypromine, and selegiline. These medications can work well for some people with treatment-resistant or atypical depression, but they require strict attention to drug interactions and dietary restrictions.
People taking certain MAOIs must avoid high-tyramine foods such as aged cheeses, cured meats, and some fermented products because dangerous blood pressure spikes can occur. MAOIs can also interact with many medications and supplements. In other words, this is not the antidepressant class for people who enjoy improvising at the pharmacy counter.
7. Esketamine and Treatment-Resistant Depression Options
For adults with treatment-resistant depression, esketamine nasal spray may be considered under medical supervision. It is given in certified healthcare settings because it can cause sedation, dissociation, and blood pressure changes. It is not a casual “take it and drive to brunch” medication.
Other options for difficult-to-treat depression may include medication combinations, augmentation with other psychiatric medications, electroconvulsive therapy, transcranial magnetic stimulation, intensive outpatient programs, or specialized psychiatric care. Treatment-resistant depression does not mean hopeless depression. It means the treatment plan needs a more advanced toolbox.
How Doctors Choose the Right Antidepressant
There is no single best antidepressant for everyone. A doctor considers symptoms, medical history, age, pregnancy or breastfeeding status, other medications, family response to antidepressants, side effect concerns, sleep patterns, appetite, anxiety level, cost, insurance coverage, and patient preference.
For example, someone with depression, panic attacks, and poor appetite may be approached differently from someone with depression, fatigue, and sexual side effect concerns. A person with high blood pressure may need extra caution with some SNRIs. Someone with bipolar disorder symptoms needs careful evaluation because antidepressants can sometimes trigger mania or hypomania if bipolar disorder is untreated.
This is why “my cousin loved this medication” is interesting but not medically decisive. Your cousin may also love pineapple on pizza. Helpful information? Maybe. A universal law? Absolutely not.
Common Side Effects of Antidepressants
Side effects vary by medication and person. Common antidepressant side effects include nausea, headache, dry mouth, dizziness, constipation, diarrhea, sweating, sleepiness, insomnia, appetite changes, weight changes, emotional blunting, and sexual problems such as reduced desire, delayed orgasm, or erectile difficulty.
Many early side effects improve after the first few weeks. When side effects do not improve, clinicians may adjust the dose, change the timing, switch medications, add supportive treatment, or choose a different drug class. Patients should not stop antidepressants suddenly unless a clinician instructs them to do so, because abrupt stopping can cause discontinuation symptoms such as dizziness, flu-like feelings, irritability, insomnia, nausea, and electric-shock sensations sometimes called “brain zaps.”
Important Safety Considerations
Antidepressants carry an FDA boxed warning about increased risk of suicidal thoughts and behaviors in children, adolescents, and young adults, especially during the first months of treatment or after dose changes. This does not mean antidepressants are forbidden for younger people. It means careful monitoring is essential.
Anyone starting antidepressant treatment should watch for worsening depression, agitation, panic, impulsivity, unusual mood elevation, severe insomnia, or suicidal thoughts. Family members and close friends can help notice changes early. If suicidal thoughts feel urgent or a person may act on them, emergency help is needed immediately.
Another rare but serious risk is serotonin syndrome, which can happen when serotonin levels become too high, often because of medication combinations. Symptoms may include fever, confusion, agitation, sweating, diarrhea, tremor, muscle stiffness, and rapid heart rate. People should tell their doctor about all prescriptions, over-the-counter medicines, supplements, and recreational substances before starting an antidepressant.
How Long Should Someone Take Antidepressants?
The length of treatment depends on the person. For a first episode of depression, clinicians often recommend continuing medication for several months after symptoms improve to reduce relapse risk. People with recurrent depression, chronic depression, severe episodes, suicidal history, or strong family history may need longer treatment.
Stopping medication should be planned, gradual, and supervised. A good taper considers the dose, medication half-life, treatment duration, previous withdrawal symptoms, and whether life is currently stable. Tapering during a divorce, final exams, job loss, or a week when the washing machine explodes may not be ideal timing.
Antidepressants and Therapy: Better Together?
Medication can reduce symptoms, but therapy can help people understand patterns, build coping skills, process trauma, improve relationships, challenge depressive thinking, and create relapse-prevention strategies. Cognitive behavioral therapy, interpersonal therapy, behavioral activation, problem-solving therapy, and mindfulness-based approaches can all be part of depression care.
For mild depression, therapy or lifestyle-focused treatment may be an appropriate first step for some people. For moderate to severe depression, medication and therapy together are often recommended. The most effective plan is usually the one a person can actually follow consistently.
Lifestyle Support While Taking Depression Medication
Antidepressants do not cancel the need for daily care. Sleep, nutrition, movement, sunlight, social connection, reduced alcohol use, and treatment of medical problems can all influence recovery. Exercise does not have to mean becoming a person who owns twelve types of athletic shoes. A ten-minute walk, stretching, or basic strength training can help build momentum.
Patients should also avoid alcohol or use it cautiously, because alcohol can worsen depression, interfere with sleep, and increase medication side effects. Regular follow-up appointments matter too. Depression treatment is not “take pill, vanish from doctor, hope for best.” It is a process of tracking symptoms, side effects, function, and quality of life.
Real-World Experiences With Depression Medications
Because depression medications work differently for different people, the lived experience is often more nuanced than a simple success-or-failure story. Consider a composite example: Maya starts an SSRI after months of waking at 3 a.m., crying before work, and losing interest in friends. During the first week, she feels nauseated and wonders if the tiny tablet is personally offended by her stomach. Her doctor suggests taking it with food and checking in after two weeks. By week four, she is not “cured,” but she notices she can shower, answer messages, and laugh at a sitcom again. That matters.
Another composite example is Daniel, whose depression looks less like sadness and more like a dead battery. He sleeps too much, avoids calls, and cannot focus. An SSRI helps his anxiety but leaves him with sexual side effects and emotional flatness. Instead of quitting suddenly, he tells his clinician. They adjust the plan and eventually try bupropion. His energy improves, and the side effects are more manageable. The lesson is not that one drug is better for everyone. The lesson is that honest feedback helps doctors tailor treatment.
Then there is the person who tries the first antidepressant and feels worse: more restless, more wired, unable to sleep. That can happen. Sometimes it is a dose issue. Sometimes it is the wrong medication. Sometimes it reveals an underlying bipolar spectrum condition that needs a different approach. This is why follow-up is not optional decoration; it is part of safe prescribing.
People also describe emotional adjustment after improvement. When depression has been present for years, feeling better can be oddly unfamiliar. Some patients say they expected fireworks but instead got the quiet ability to do laundry, cook dinner, and answer a text without needing a three-hour recovery period. Recovery may look boring from the outside. From the inside, boring can be beautiful.
Another common experience is impatience. Someone starts medication on Monday and wants to feel better by Wednesday because life is still happening, bills are still due, and the dog still expects walks. Unfortunately, antidepressants usually require patience. Keeping a simple mood log can help. Tracking sleep, appetite, energy, anxiety, side effects, and daily functioning gives patients and clinicians better information than relying on memory alone, especially because depression is famous for whispering, “Nothing has changed,” even when small improvements are happening.
Finally, many people learn that medication is not a moral statement. Taking an antidepressant does not mean someone is weak, broken, dramatic, or incapable of handling life. It means they are treating a medical condition with available tools. Some people use antidepressants temporarily; others use them long term. Some need therapy first; others need medication urgently. Some need both. The goal is not to win a toughness contest. The goal is to stay alive, function better, suffer less, and slowly rebuild a life that feels worth participating in.
Conclusion
Depression medications can be life-changing, but they work best when chosen carefully, monitored properly, and combined with realistic expectations. SSRIs and SNRIs are common first-line antidepressant drugs, while bupropion, mirtazapine, trazodone, TCAs, MAOIs, esketamine, and newer options may be useful in specific situations. Side effects are real, but many can be managed. Treatment may require patience, adjustment, and teamwork.
The most important message is simple: depression is treatable, and needing medication is not a character flaw. If depression has made life feel smaller, heavier, or harder to navigate, professional help can open the door to recovery. No one should have to negotiate with depression alone while pretending everything is fine. Even the strongest people need support, and sometimes that support comes in the form of therapy, community, better sleep, honest conversations, and yes, a carefully chosen prescription bottle.