If your healthcare provider has ordered an ACTH (cosyntropin) stimulation test, chances are you have one big question and several smaller, more panicked ones. What does it test? Why do I need it? Will I be fasting, fainting, or dramatically clutching a waiting-room chair?
The good news: this test is usually short, straightforward, and incredibly useful. The less-fun news: it is often ordered when a provider wants to find out whether your body is making enough cortisol, one of the hormones that helps you handle stress, maintain blood pressure, regulate blood sugar, and generally keep the engine running without dashboard lights flashing.
In simple terms, the ACTH stimulation test checks how well your adrenal glands respond when they are given a synthetic version of ACTH, a hormone that normally tells them to produce cortisol. Think of it as a professional roll call. The pituitary sends the message, the adrenals are supposed to answer, and the lab results reveal whether the response is normal, weak, delayed, or suspiciously quiet.
This guide explains what the cosyntropin stimulation test is, why it is ordered, how to prepare, what the results may mean, and what real-world experiences often feel like from the patient side of the exam chair.
What Is the ACTH (Cosyntropin) Stimulation Test?
The ACTH stimulation test is a dynamic hormone test used to evaluate whether the adrenal glands can produce enough cortisol after being stimulated. The medication used is cosyntropin, a synthetic form of ACTH. You may also hear it called a Cortrosyn stimulation test, test of adrenal reserve, or simply an adrenal insufficiency test.
This matters because cortisol is not some background extra in your hormone cast. It plays a leading role in how your body responds to physical stress, illness, injury, low blood pressure, low blood sugar, and inflammation. When cortisol production is too low, the consequences can range from ongoing fatigue and dizziness to a dangerous emergency called adrenal crisis.
The ACTH stimulation test is different from a basic cortisol blood test. A single cortisol value can be helpful, but it is just a snapshot. The stimulation test asks a more revealing question: Can your adrenal glands respond when they are told to get moving?
Why Would a Doctor Order This Test?
Healthcare providers usually order an ACTH stimulation test when they suspect adrenal insufficiency or need to clarify a low or borderline cortisol result. It may also be used after long-term glucocorticoid treatment to see whether the body’s normal hormone system is recovering.
Common reasons for testing include:
- Unexplained fatigue or weakness
- Low blood pressure or dizziness, especially when standing
- Unintentional weight loss
- Abdominal pain, nausea, or poor appetite
- Low blood sugar, especially in children
- Darkening of the skin in suspected Addison’s disease
- Concern about pituitary problems affecting ACTH production
- Checking recovery after prolonged steroid use, such as prednisone or hydrocortisone
The test is most often used to help evaluate three related problems:
1. Primary adrenal insufficiency
This happens when the adrenal glands themselves are damaged and cannot produce enough cortisol. Addison’s disease is the classic example.
2. Secondary adrenal insufficiency
This happens when the pituitary gland does not make enough ACTH, so the adrenal glands are not properly stimulated.
3. Tertiary adrenal insufficiency
This starts one step higher in the chain, in the hypothalamus. It is often discussed along with secondary adrenal insufficiency because the downstream result is still reduced cortisol production.
In some settings, the ACTH stimulation test may also help evaluate nonclassic congenital adrenal hyperplasia, especially when a doctor is looking for specific adrenal enzyme problems. So yes, the test has range. It is not a one-trick hormone pony.
How the Test Works
The process is usually simple and takes roughly 30 to 90 minutes, depending on the protocol used at the clinic or lab.
Typical step-by-step process
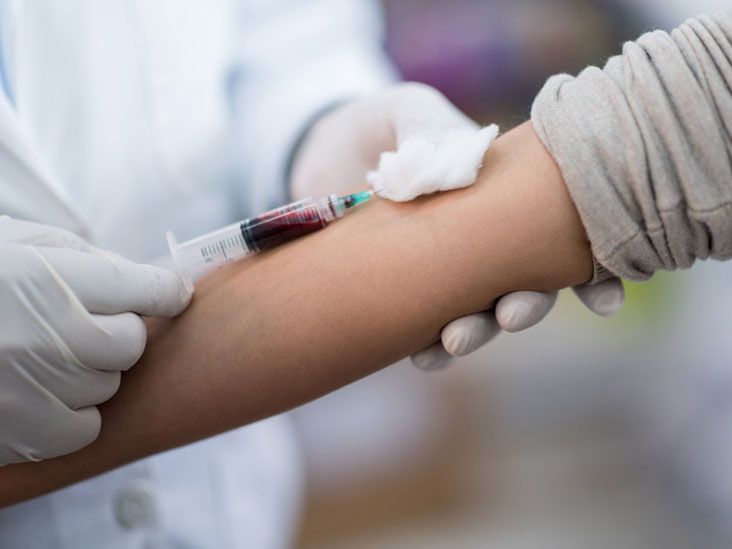
- A baseline blood sample is drawn to measure your cortisol level. Some providers also order baseline ACTH or other hormone tests at the same time.
- You receive an injection of cosyntropin, either into a muscle or through an IV.
- Additional blood samples are collected at specific times, usually 30 minutes, 60 minutes, or both.
- The lab compares your cortisol level before and after stimulation.
The goal is not to see whether cortisol exists at all. The goal is to see whether it rises appropriately after the adrenal glands receive the hormonal nudge.
Some labs use a standard 250 mcg cosyntropin dose. The exact timing and interpretation may vary by protocol, the assay used, and the clinical question your doctor is trying to answer.
How to Prepare for an ACTH Stimulation Test
Preparation is one of those “follow your provider’s instructions, not your cousin’s group chat” situations. Still, there are a few common guidelines.
You may be told to:
- Fast for about 6 hours before the test
- Limit strenuous activity beforehand
- Eat a higher-carbohydrate diet in the 12 to 24 hours before testing
- Temporarily stop certain medications that can interfere with cortisol results
- Come in in the morning, since cortisol naturally peaks earlier in the day
That medication part is especially important. Steroids such as hydrocortisone, prednisone, prednisolone, methylprednisolone, and dexamethasone can affect testing or interpretation. Estrogen therapy, pregnancy, and severe stress can also influence cortisol readings. Never stop a prescription medication on your own just because the internet made eye contact with you. Ask your clinician exactly what to hold and when.
What Does the Test Feel Like?
Most people describe the ACTH stimulation test as more annoying than dramatic. There is a blood draw, an injection, and then more waiting than glamour. The needle stick may feel like a pinch. The injection can sting a bit. Some people feel mildly flushed, nervous, or nauseated afterward. Others feel absolutely nothing except bored.
Possible minor effects include:
- Brief discomfort from the blood draw
- Mild bruising or tenderness at the needle site
- Temporary flushing
- Lightheadedness
- Nausea
Serious reactions are uncommon, but allergic-type symptoms such as hives, swelling, wheezing, or trouble breathing require immediate medical attention.
What the Results May Mean
This is the part where everyone tries to become their own endocrinologist in a patient portal at 11:47 p.m. Resist the urge. ACTH stimulation test results can be nuanced.
In general:
- A normal rise in cortisol usually means the adrenal glands are responding appropriately.
- A blunted or absent rise may suggest adrenal insufficiency, adrenal suppression, or reduced adrenal reserve.
Historically, many labs used a stimulated cortisol cutoff around 18 mcg/dL. However, newer cortisol assays may use lower thresholds, often around 14 to 15 mcg/dL. That means the “normal” cutoff is not universal. It depends on the lab method, the assay, the sample timing, and the broader clinical picture.
This is why one of the most important takeaways is also the least exciting: your result must be interpreted in context. A number alone does not tell the whole story.
Other factors that matter
- Your baseline ACTH level
- Symptoms and physical exam findings
- Whether you have been taking steroids
- Whether pituitary disease is suspected
- How recently secondary adrenal insufficiency may have started
- Which cortisol assay the lab used
One important limitation: the ACTH stimulation test can miss early secondary adrenal insufficiency. If the pituitary has only recently stopped making enough ACTH, the adrenal glands may still respond normally for a while. In those cases, a doctor may order repeat testing or use a different test, such as an insulin tolerance test or a CRH stimulation test.
Can the Test Diagnose Addison’s Disease?
It can strongly support the diagnosis, but it is usually one piece of the puzzle rather than the entire puzzle box. If the test suggests primary adrenal insufficiency, your doctor may also order:
- ACTH blood levels
- Aldosterone and renin testing
- Electrolyte testing, especially sodium and potassium
- Antibody testing for autoimmune Addison’s disease
- Imaging in selected cases
That broader workup helps identify not only whether cortisol is low, but also why it is low. That distinction matters because primary, secondary, and tertiary adrenal insufficiency do not all have the same cause, treatment approach, or long-term monitoring plan.
When the Test Is Especially Helpful After Steroid Use
Long-term glucocorticoid therapy can suppress the hypothalamic-pituitary-adrenal axis. In everyday language, the body gets used to outside steroid medication and may temporarily slow its own cortisol signaling. When steroids are reduced or stopped, doctors sometimes use the cosyntropin stimulation test to check whether the adrenal glands are ready to resume normal function.
This is one reason the test shows up in very different clinical settings. One person is being evaluated for Addison’s disease. Another is recovering after months of prednisone. Same test, different story, same waiting room chairs.
When to Seek Urgent Medical Care
If adrenal insufficiency is suspected and you have symptoms of adrenal crisis, testing should not delay treatment. Adrenal crisis is a medical emergency.
Warning signs include:
- Severe weakness
- Vomiting or diarrhea with inability to keep medication down
- Confusion
- Fainting
- Very low blood pressure
- Severe abdominal pain
- Dehydration
- Loss of consciousness
If those symptoms happen, urgent treatment with corticosteroids and IV fluids comes first. Lab confirmation can follow later.
Bottom Line
The ACTH (cosyntropin) stimulation test is one of the most useful tools for evaluating adrenal function. It helps determine whether your adrenal glands can respond properly to ACTH and produce enough cortisol. It is commonly used when doctors suspect adrenal insufficiency, need to investigate a low cortisol level, or want to assess adrenal recovery after steroid treatment.
The test itself is usually quick. The interpretation is the part that deserves patience and expertise. Cutoffs vary, medication history matters, and early pituitary-related disease can be tricky. So while the procedure may take less than an hour, the meaning of the result belongs in a bigger medical conversation.
In other words, the test may be short, but it asks a very important question: When your body gets the signal to make cortisol, can it answer?
Experiences Related to the Topic “ACTH (Cosyntropin) Stimulation Test”
For many patients, the hardest part of the ACTH stimulation test is not the injection. It is the uncertainty leading up to it. People often arrive at the test after weeks or months of symptoms that are frustratingly vague: crushing fatigue, brain fog, dizziness, nausea, salt cravings, or the strange feeling that their body is no longer cooperating with ordinary life. Because those symptoms overlap with many other conditions, being told you need a hormone stimulation test can feel both validating and unnerving. On one hand, finally, someone is checking something specific. On the other hand, the name alone sounds like it belongs in a medical drama soundtrack.
A common patient experience is surprise at how ordinary the test setup actually looks. There is no giant machine, no dramatic countdown, and no sci-fi chamber glowing in endocrine blue. Usually, it is a chair, a blood draw, an injection, more blood draws, and some waiting. Many people say the experience feels more like a carefully timed lab visit than a major procedure. The most frequent complaints are practical ones: fasting, adjusting medications, finding a morning appointment, and sitting still while hoping the veins cooperate.
Emotionally, people often describe two very different reactions to the results. If the response is normal, there is sometimes relief mixed with confusion. Relief, because severe adrenal failure becomes less likely. Confusion, because the original symptoms are still real and still need an explanation. A normal test can close one door while leaving several others wide open. That can be frustrating, especially for people who were hoping for a quick answer and a neat label.
For patients whose results are abnormal or borderline, the experience can become more layered. Some feel relieved to finally have objective evidence that something is wrong. Others feel overwhelmed because the next step may involve more testing, daily steroid replacement, sick-day dosing instructions, medical alert identification, or learning how to respond in an emergency. In those cases, the ACTH stimulation test is less of a finish line and more of an introduction to a new medical vocabulary.
People who have taken long-term steroids often describe a different emotional experience. For them, the test is not always about discovering a brand-new condition. It is often about recovery, uncertainty, and whether the body’s own cortisol system is waking back up. That can create a strange mix of hope and caution. Patients may feel physically better than before but still worry about whether illness, injury, or surgery could expose hidden adrenal suppression.
One of the most useful things patients say afterward is that clear instructions matter almost as much as the lab value itself. Knowing whether to hold medication, whether to fast, what the timing means, and when to expect results can make the experience feel far less intimidating. The test may be short, but the questions around it are usually not. Good communication turns the ACTH stimulation test from a mysterious hormone ambush into what it really is: a focused tool that helps doctors understand how your stress-response system is functioning.